

Note: a significant portion of this post (e.g., the charts), in particular this section, came from Jim West, a journalist who put a great deal of work into this subject (and has written detailed books and an extensive article on it). While the research in this section is quite compelling, given its nature, it will likely be quite difficult for many of you to read.
Due to an unusual confluence of historical and cultural factors (e.g., a 1984 state plan), in the late 1980s, China, was eager to utilize its newfound scientific apparatus (which, unlike now, had not yet been captured by conflicts of interest). In turn, a series of studies were conducted that would never be done in the West, which provided the definitive proof US is not safe during pregnancy.
Essentially, they took large numbers of women planning to have abortions (which due to the One Child policy—a tragic period I wrote much more about here—were frequently done to both willing and unwilling mothers), gave US to half of them, and then dissected the aborted fetuses to assess if US had damaged them. To quote one of the lead investigators:
In view of the favorable conditions of China’s basic national policy of family planning, Gong Yan and others from Xi’an Medical University took the lead in completing the first clinical study in China.
In my eyes, it is tragic both that these studies happened and that this knowledge has been completely forgotten. As you read these, it’s important to keep in mind that they used dramatically lower US doses than what the FDA now permits.
Overviews
Starting in 1986, professor Rou Feng began publishing studies raising concerns about the urgency of determining the safety of US in pregnancy.
In 1998 Rou Feng published a paper (which can be read here) that highlights the dangers of US (e.g., heat damage, cavitations, sound pressure, acoustic radiation forces). To quote (a machine translated) version of it:
This issue has become very important and eye-catching since the 1980s. One of the backgrounds is the rapid expansion of the application scope of diagnostic ultrasound in obstetrics and the other is that the transient sound intensity output by diagnostic ultrasound equipment may sometimes be as high as 1000w/cm2 or more. Such high sound intensity is enough to produce cavitation in organisms containing cavitation nuclei.
Once cavitation occurs, as Professor Carstensen pointed out: “... the effect caused by cavitation may be very local, damaging only a few cells around it. For most organs or biological fluids in the human body, damaging a small number of cells will not affect health , but the only exception is when it involves human reproductive cells. Or embryos or fetuses in a sensitive period of development, in this case, even if a few cells are damaged, the public will find the consequences of this unacceptable.# Internationally, research on the safety threshold dose of diagnostic ultrasound is mainly carried out through two channels: experimental animals and epidemiological research. The research is extensive, sometimes even cross-border, and a lot of research data has been accumulated. A small number of quantitative laws have also been summarized, but at best it can only serve as a reference for clinical safety diagnosis, and it is impossible to provide specific guidance standards.
To be precise, establishing the safety threshold dose standard for diagnostic ultrasound should be based on a large number of scientific studies on obstetric clinical ultrasound diagnosis, which is a gap in international research. This is a major shortcoming!
Note: Rou Feng has also published studies (e.g., this one) about high powered US being used to eliminate tissue (e.g., uterine lining) that can be viewed in English databases.
This 2001 review paper provides a detailed overview of the harms of prenatal US and includes a focus on the appropriate dosing of ultrasound.
This 2005 review paper identified 130 English and 35 Chinese articles published between January 1998 to January 2004 on US and apoptosis (cell death). Collectively they showed US had dose dependent biological effects such as inducing apoptosis and that there was inadequate research to ensure its safety for humans.
This 2010 review paper focuses on the biological effects of pregnancy US in humans and animals (e.g., changes and injuries to organs, tissues, cellular ultrastructures, and cytokines), highlighting a dose-response relationship, the sensitivity of tissues and cells to US, and that both acute reversible and irreversible apoptotic processes are initiated by US.
Note: apoptosis describes the programmed death processes many cells go through after facing hostile environments or signals from the body, while apoptotic proteins denote those that facilitate the process.
Chorionic Villus
Note: the chorionic villi are projections from the placenta that contain the same genetic material as the fetus, and hence are frequently sampled to get the fetus’s genetic information without gouging out part of the developing baby. In theory, this represents the best way to evaluate the effects of US on fetuses, as those cells can be obtained and dissected without aborting the baby. However, in some of these chorionic villi studies, it specified an abortion was performed shortly after.
A 1992 study of 55 early pregnant women US found that 20 minutes or more of US caused lipid peroxidation, increased malondialdehyde levels and decreased glutathione peroxidase levels, and that these changes were dose dependent.
A 1992 study of 15 healthy women at 6 to 8 weeks of gestation found that US caused pyknosis (shrinkage), disintegration, and increased vacuolization of the syntrophoblast (ST) cells and necrosis in part of the villi (with slight changes being observed after 10 minutes and significant ones after 30 minutes).
A 1994 study (which is in Pubmed) found that US for 5, 10, or 30 minutes (at 6-8 weeks of gestation) caused cellular changes including hyperreaction of lipid peroxides; increased activities of some lysosomal enzymes; reduced SOD activity; and vesiculation and aberration of some mitochondrion, also transformation or disappearance of some microvilli in ultrastructure, and that these effects were increased with US exposure time.
A 1995 study of 9 early pregnancy women found 10 but not 5 minutes of transvaginal US caused breaking, loss and disorganization of the microvilli and expansion of rough endoplasmic reticulum.
A 1995 study of 40 embryos (with the US in B-mode) found that at 5 minutes of US caused subtle changes, whereas at 10, 20 and then 30 minutes, increasing cellular damage was seen (e.g., swelling, degenerating and necrotic cells). The authors concluded that US should ideally be limited to 1 minute or less.
Note: the authors also advocated for mothers to have a full bladder during the procedure as this increases the distance between the mother and the fetus and that multiple US examinations should be avoided if at all possible.
A 1995 study gave US to 27 healthy women at 40-60 days gestation who received 0-15 minutes of US and then evaluated the villus 7 days later. It found 10 but not 5 minutes of US, in a dose dependent manner, caused injury and deformation of the plasma membrane, the deformation, shrinkage and breaking of microvilli, shrinking or swelling of components of the cells, and focal necrosis or karyolysis. It also found that broad bandwidth US was more damaging than single frequency US and that US was less damaging later in pregnancy.
A 1996 study (which is in Pubmed) found that after 30 minutes, compared to controls, 0.7mW/cm2 of either B-mode or color Doppler US caused expansion of perinuclear space in cytotrophoblasts [CTs] and [STs], enlargement of rough endoplasmic reticulum, and vacuolization in the cytoplasm.
A 1998 study gave 125 early pregnancy women 0, 10, 20 or 30 minutes of US and then analyzed the CV 7-10 days later. At 20 minutes, malondialdehyde (a reactive molecule that damages cells) was increased and GSH px (an enzyme that protects cells from oxidants) was decreased, while at 30 minutes, DNA content was decreased. After 7-10 days, these figures normalized.
A 1999 study (which can also be viewed on PubMed) gave 80 women, no US, 10 minutes of US through the abdomen, 3 minutes of US through the vagina, or 10 minutes through the vagina (a stronger route of fetal US exposure). An hour later, embryo villi were obtained through abortions and 10 minutes of transvaginal ultrasound was found to cause the microvilli to become broken, lost, and disarranged, and the rough endoplasmic reticulum of trophoblasts became expanded. Additionally, their malondialdehyde levels increased and the superoxide dismutase (SOD) decreased.
A 2001 study found US decreased the activity of SOD (a key antioxidant enzyme of the body).
A 2001 study exposed 24 first trimester women to varying amounts of Doppler US then after 24 hours, their trophoblasts were removed and analyzed for their rates of apoptosis.
. In controls, the apoptotic rate was 44.56% [±13.24] in the syncytiotrophoblasts (STs) and [43.14] ± 11.76, in 20 minutes in the cytotrophoblasts (CTs) while after 30 minutes, 59.64% [±11.85] in the STs and 61.43% [±10.13] in the CTs.
Note: no increase from controls was observed in the 10 minute US group, but an increase was observed in the 20 minute group (which was greater in the 30 minute one).
A 2001 study found US significantly lowered nitric oxide (an important molecule for health) and the enyzme that synthesizes it.
A 2001 study used electron microscopy and flow cytometry to assess how US induced apoptosis. Control cells had spheroid nucleus with unstained and dispersed chromatin and abundant cytoplasm. US caused the nucleus to shrink, for patches of condensed chromatin to line the nuclear membrane, and in time the nuclear membrane to become stuck to the nucleus causing it to clump (and also increased the ratio of apoptotic cells).
A 2002 study exposed 24 first trimester women to varying amounts of Doppler US, then after 24 hours, their trophoblasts were removed and analyzed for their Fas/FasL mRNA expression (a receptor that triggers the cell death process). In controls (0 minutes US), there was a 58% [±5] rate of Fas expression in the STs and 52% [±5] in the CTs and for FasL, 63% [±6] in the STs and 62% [±12] in the CTs. No significant difference was seen with 10 minutes of US, however, a significant increase was seen with 20 minutes (e.g., FasL expression reached 74% [±10] in the STs and 72% [±12] CTs) and at 30 minutes (e.g., Fas expression reached 70% [±6] in the STs and 65% [±9] CTs).
A 2002 study of 15 women at 6-8 weeks gestation found that 20 but not 10 minutes (or less) of US caused enlargement of endoplasmic reticulum and mitochondrial intracristal space in syntrophoblast cells.
A 2002 study (which is in PubMed) found that 20 minutes but not 10 minutes of 13mW/cm2 transvaginal US in 4 hours activated caspase-3 (which induces apoptosis), released cytochrome C from the mitochondria (indicating mitochondrial damage) and fragmented DNA.
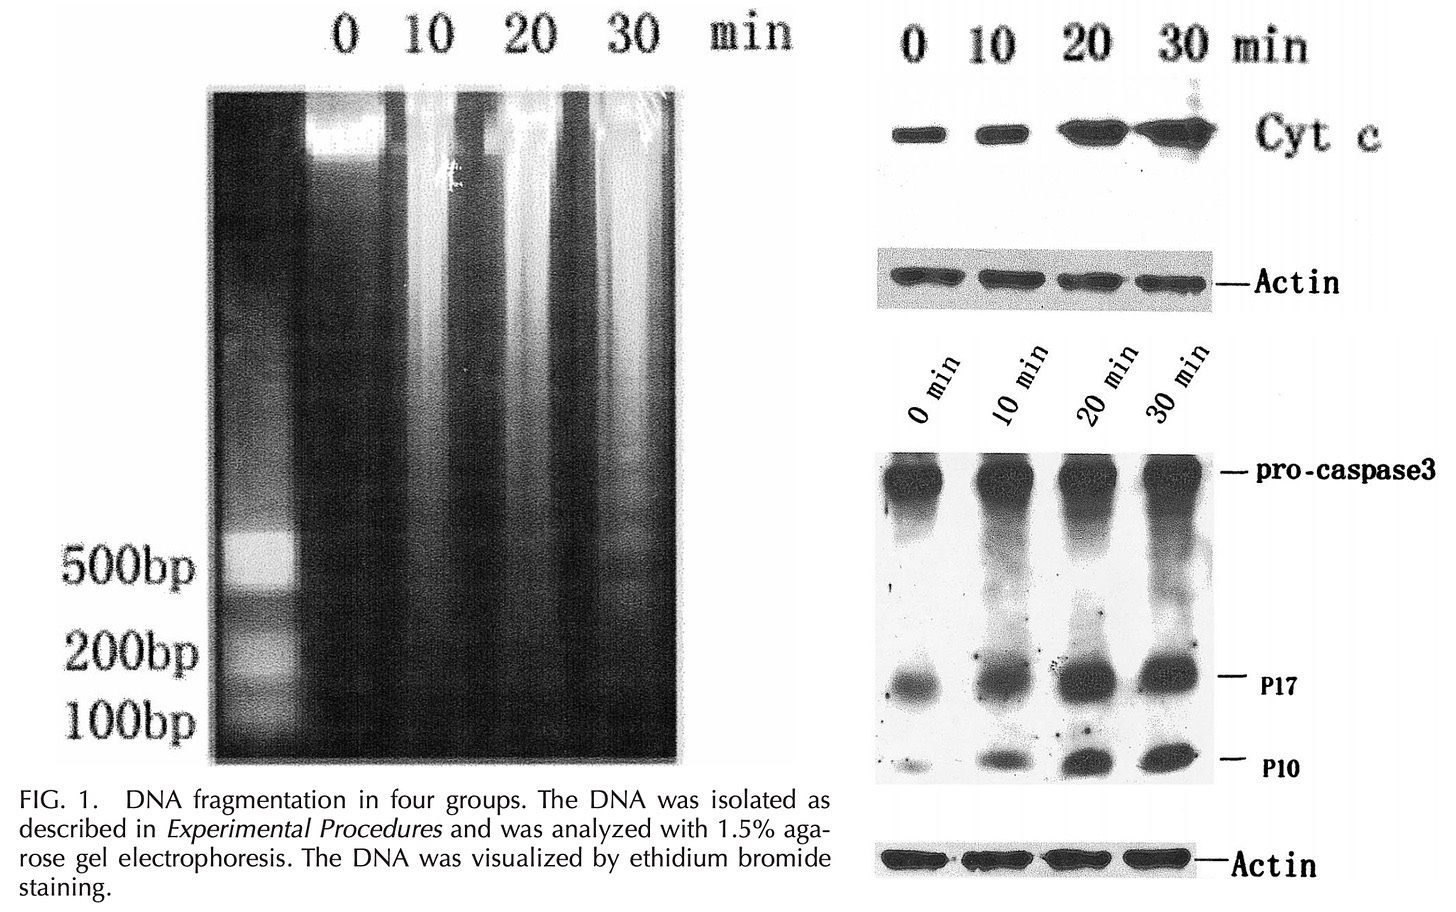
A 2005 study gave US to 24 first trimester women and found that 10 minutes created no changes in Capase 3 and 8 protein expression, but after 20 minutes (and 30 minutes) both apoptotic proteins increased.
A 2006 study of 66 early pregnant women found that 5 minutes or more of transabdominal US significantly increased the expression of mRNA for Caspase-3 (which plays a key role in apoptosis). Additionally, the authors suspected a smaller amount of time with transvaginal US could trigger these changes.
A 2006 study exposed 27 healthy pregnant women (at 40-60 days gestation) to either 0, 5, 10 or 15 minutes of US, and found that those who’d received 10 or more minutes of US had varying degrees of dose-dependent damage the syntrophoblast and trophoblast cells such as injury and deformation of the plasma membrane, shrinking or swelling of the cell, focal necrosis, and karyolysis. Additionally, they found that broad bandwidth US caused more damage, and that this damage decreased evidently after 7 days.
A 2006 study of 10 first trimester women transvaginal US, and found that compared to 5 controls (who rarely underwent apoptosis—something also observed in many of the other studies I’ve listed), it caused apoptosis in a dose dependent manner which gradually returned to normal after 72 hours.
A 2006 study of 35 early pregnancy women found that at least 15 but not 5 minutes of transabdominal US caused immediate and significant cellular damage, and that at least 10 minutes of US caused increased RNA expression for Caspase-3 (an apoptotic protein) and Livin-α (a protein that is overexpressed in many cancers).
A 2008 first trimester study found that US caused apotosis in a dose dependent manner for 72 hours after US that was not present in controls.
A 2008 study gave transvaginal US to 60 healthy first trimester women. It found that 3 minutes decreased the expression of Bcl-2 (a protein that prevents apoptosis), at least 5 minutes (but not 3), when assessed 24 hours later, caused apoptosis of chorionic villi, and that 10 minutes further increased the apoptosis and also increased the expression of Bax (another protein that facilitates apoptosis). Like many other of these studies, it emphasized that caution should be given with pregnancy and US, that the probe should not be held in the same position for a prolonged period and that US should be under 3 minutes in total.
A 2009 study gave US to 65 first-trimester women, and then assessed their chorionic villi TNF-α and p55 TNF receptor expression 24 hours later (they are key mediators of inflammation and apoptosis). In controls, they were 54.26% [±6.48] and 61.56% [±9.23] respectively, after 10 minutes, 55.54% [±2.82] and 62.75% [±11.84], after 20 minutes 61.94% [±6.34] and 67.38% [±8.77], after 30 minutes 65.39% [±5.96] and 74.63% [±7.38].
A 2010 study of 50 pregnant women found that approximately 10 minutes of transvaginal US caused cellular damage to the villi, whereas 5 minutes of exposure resulted in it being “basically normal.”
Brain
A 1998 study (archive link) of 28 pregnant women found 30 minutes but not 10 minutes of US caused the fetal pituitary gland to have paravessel tissue edema, the space between the cells there to increase, its cells to have rarefaction of their nuclear chromosomes, and its mitochondria to vacuolize.
Note: we suspect widespread pituitary gland dysfunction (possibly due to US or vaccine induced microstrokes) is a key culprit in the obesity and diabetes epidemic.
A 2002 study of 8 women at 18-25 weeks (4 of whom were controls) gave 4 of them 10 minutes of 124.1mW/cm2 B-mode US (directed at the fetus’s brain) 30 minutes prior to abortion. Compared to controls, this caused the brain’s neurons to have irregularly distributed chromatins (which became condensed or marginated), depleted glycogen (few particles were in cytoplasm), frequent secondary lysosomes, and some of the mitochondria to be swollen slightly or even vacuolated.
A 2005 study of 10 pregnant women (at 18-25 weeks gestation) found giving 10 minutes of B-mode US 30 minutes prior to abortion harmed the brain’s glial cells. Specifically, glial cell membranes, subcellular organelles such as mitochondria, Golgi complex, and endoplasmic reticulum appeared damaged, the perinuclear space was widened, chromatins were distributed irregularly, markedly condensed, and agglomerated (which is a characteristic of apoptosis).
Eyes
A 1997 study of 80 pregnant women found that 5 minutes of US resulted in local edema of the fetus’s cornea and after 20 minutes (but not 10 minutes), resulted in the antioxidant activity (SOD and GSH-Px) of the villous cells decreasing
A 2001 study of 90 pregnant women (with controls) found that 3 minutes of US caused local edema of the fetal cornea and after for 20 mins resulted in corneal SDH (a mitochondrial enzyme) values decreasing.
Immune Function
A 1994 study found that giving women of any trimester US (at 7.6mW/cm2) for 30 minutes resulted in the newborns red blood cell C3b receptors being decreased and the formation red blood cells rosette immune complexes was increased.
Kidney
A 2002 study found that exposing second trimester fetuses to 10 minutes of US immediately prior to abortion did not affect the kidneys. However, 30 minutes of US resulted in the kidneys (48 hours later) caused an irregular distribution of nuclear chromosomes of the cells of the renal glomerulus and renal tubule, the mitochondria to swell and expand, the mitochondrial crest to disappear and vacuolated and the rough endoplasm reticulum to slightly expand.
Liver
A 2004 study (archive link) of 36 women near the middle of their pregnancy gave US 48 hours prior to abortion. It found 30 minutes of US but not 10 minutes caused the liver mitochondria to swell and have blurred cristae.
Reproductive Organs
A 1996 study of 36 pregnant mothers (at 20-28 weeks gestation) found 30 minutes but not 10 minutes of US caused the cells of the testicles that produce sperm (the spermatogonia) to become swollen, have a rarefaction of nuclear chromosomes and to have damaged mitochondria.
Note: identical results were obtained from another 1995 study.
A 1997 study of approximately 70 aborted fetuses at 16-28 weeks gestation found that 30 minutes but not 10 minutes of US harmed their ovaries. Specifically, the eggs became swollen with rarefaction of the nuclear chromosome and the mitochondria became swollen, vacuolized and their cristae disappeared.
Lastly, in addition to these studies, I also identified 24 other Chinese publications demonstrating the dangers of US during pregnancy (which are listed here). These include 8 review papers, 2 on US triggering mutagenesis, 8 on its effect on the chorionic villus, 2 on its effects on the eyes, 2 on the immune system (one for the decidua, and one for the neonate shortly after birth), and 2 on the testicles. Since I could not provide a link to them, I did not list them here, but if anyone can, that would be greatly appreciated, and they will be added to this article.
Overview Studies
Canal Cui, and Min Xia, “Research On The Impact Of Fetal Development B-Mode Ultrasound”, China Eugenics Journal, April 1998.
Ruo Feng, “Obstetric Ultrasound Image Diagnosis Latest Research Safety - To Participate In October 1988 Opinion Of The Meeting In Washington WFUMB,, Chinese Journal Of Ultrasound In Medicine, April 1989.
Ruo Feng,“Diagnosis Of Intrauterine Fetal Ultrasound On Embryonic Dose Safety Studies, Article: My Opinion”, Chinese Journal of Ultrasound in Medicine, 6, no. 3 (1990): 210-11
Ruo Feng, Hua Mao Li, “Pregnancy Ultrasound Image Diagnos is Safe”, Nature Journal, 1990, 669-73.
Ruo Feng, “Biological Effects Of Ultrasound And Ultrasound Dosimetry”, Ultrasound in Medicine, Third Edition, Beijing, Science Press, 1998, 57-74, Guo Zhou Yong, Science Editor.
Ruo Feng, “Biological Effects Of Ultrasound And Diagnostic Ultrasound Safe Threshold Dose”, Institute of Acoustics, Nanjing University, State Key Laboratory of Modern Acoustics, 2000.
Ming Lang Peng, Ying Konggiu, and Ruo Feng,“Impact Of Diagnostic Ultrasound On Human Fetal Safety”, Chinese Journal of Ultrasound in Medicine, 13, no. 8 (1997): 51-53.
Yunhe Cui, Xianshu Tian, and Jing Guan,“An Assessment Of The Effect Of Diagnostic Ultrasound On Human Embryos”, Journal of Jinan Medical College, January 2001.
Mutagenesis
Y. Gong, YJ Zhang, and BZ Wang, “An Assessment Of The Effect Of Ultrasonic Diagnostic Dosage Of The Embryos In Utero”, J Ultrasound Med, Official Proceedings WFUMB Meeting (1988): 265-66
Liwei Zhang, “Approach to the Mutability of Diagnostic Ultrasound”, Journal of Basic and Clinical Oncology, February 1991
CVS
Rong Di Dong,“Ultrasound Diagnosis Of Radiation Impact On The Expression Of Caspase-3,8 From Human Villus Cells”, Wuhan University, 2005.
Lian-fang Du, Xiaochan High, and Kan Zhou,“Human Villi Diagnostic Ultrasound Irradiation Cell P53 mRNA Bcl-2 mRNA Expression Change”, Shanxi Journal of Medicine, May 2002
Su Fang Gao and Zuo Li,‘Apoptosis And Restoration Of Human Villi During First Trimester Pregnancy After Exposure To Transvaginal Ultrasound”, Clinical Hospital of Tianjin Medical University, 2010
Zhuang Qing Song, Hao Ning, Hung Cuifang, Hung Wang, and Meimei Wang, “Vaginal Ultrasound Early Pregnancy on Embryo Villi Apoptosis”, 2008
Shu-Ying Zhang et al.,“Ultra-wideband Diagnostic Ultrasound Influence on the Human Body and Recent Human Villi Ultrastructure Reusable”, Chinese Journal of Ultrasound Imaging, March 1995
Jun Li Zi,“A Preliminary Study On The Safety Of Diagnostic Ultrasound Human Biological Effects Villi”, Suzhou University Journal of Medical Science, 2006.
Zhuang Qing Song,“Vaginal Ultrasound Early Pregnancy on Embryo Villi Apoptosis”, 2008.
Zhang Wu, Ying Li Miao, Guorong Lu, Shuying Wu, and Fu Shao Lin, “Multiple Indicator Ultrasound Diagnosis Of Intrauterine Pregnancy Villous Impact Assessment”, China Medical Imaging Technology, January 1998.
Comprehensive (Villi, Cornea, etc)
Lang Ming Peng, Chiu Ying Kong, Cheung Chan Sung, Yu Sun, Fung if, Tsai Wen, and Guo Niangun, “Impact Of Diagnostic Ultrasound On Human Fetal Safety”, PLA Guangzhou Medical Junior College, January 1991
Lang Ming Peng, Jiashong Guo, Qiuying Kong, “Effects of Diagnostic Ultrasound Exposure to Fetal Cornea”. Journal of Branch Campus of the First Military Medical. 2000 Feb.
Immune Function
Yan Gong, Yun-Jing Zhang, and Bingsheng Wang,“Ultrasonic Influence Decidua Of Immunocompetent Cells”, Chinese Journal Of Ultrasound In Medicine, March 1991.
Xiao Hong,“Diagnostic Ultrasound Exposure Of Pregnant Women Late In Pregnancy Influence On Neonatal Immune Function”, Shanxi Journal of Medicine, 2004
Testicles
Ping Pingze,“Comprehensive Studies of Diagnostic Ultrasound On Micro-Trimester Fetal Testis Structure”, Chinese Journal of Ultrasound in Medicine, 12, no. 5 (1996): 12-14
Ultrasound irradiation of the testicles is recently being promoted for male contraception. That isirresponsible, because damaged sperm or testicles could propagate damaged offspring.
In order to qualify for care at a birth center or with a homebirth midwife, I must get an “anatomy scan” no later than 22 weeks (I am currently 18) to ensure that there are no obvious abnormalities that would exclude me from low-risk care. My plan was to ask the ultrasound technician to use the ALARA principle (as low as reasonably achievable), work as quickly as possible, and avoid directing the probe at specific parts of the baby for prolonged periods of time. Will this help to avoid major risks and damage? I do not want a hospital birth, but the anatomy scan is a requirement for all out-of-hospital birth practices in my region. I am trying my best to weigh the risks and would appreciate your input.
Maybe you could switch me to your other substack?